Why Is Lung Cancer So Difficult to Treat? Surgeon Answers
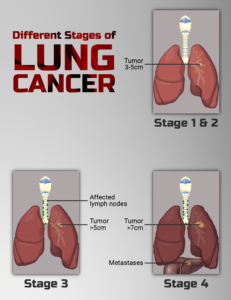
Lung cancer is one of the most terrifying cancers, one reason being that removing both entire lungs is never an option.
It’s hard to treat which is why the five-year survival rate is only 19 percent – the average when all stages of initial diagnosis are considered.
All lung cancer patients will get a treatment regimen, but the collective prognosis is bleak.
“It’s all about the stage of disease when patients are diagnosed,” says Alex Little, MD, a thoracic surgeon with a special interest in esophageal and lung cancer.
Dr. Little explains, “Roughly about 75% of patients present at initial diagnosis with stage IV (they have metastatic disease) or stage III (regional lymph nodes are involved) disease.
“Few of these patients will be cured, and I think the survival at five years is nearly zero.
“That means only a quarter of patients at diagnosis are in stage I, and are candidates for curative surgery.
“The five-year survival for these patients after surgery is about 80%. I’ve not checked all these numbers but they are reasonably accurate and would result in a five-year survival of all patients of about 19%.”
How Lung Cancer Is Treated for Different Stages – and Why It’s Difficult to Treat for Later Stages
“The challenge is to identify the patients for whom an operation is appropriate and then performing the appropriate procedure,” says Dr. Little.
“There are two aspects to this: staging the cancer and evaluating the patient’s status.
“Staging is the process by which the extent of the cancer is determined. The only reason to operate for lung cancer is the expectation that ALL the malignancy can be removed.
“If any is left—in the lung, lymph nodes or a metastatic site—the cancer will recur and the patient will not have been helped.
“Staging methods—not all are necessary in all patients—include taking a thorough history, performing a physical exam and using a battery of radiologic exams including a chest X-ray, chest computerized axial tomograph (CAT) scan, MRI scan, PET scan and biopsy of lymph nodes.
“A patient with lung cancer remaining after an operation will die of the cancer.
“But, if they respond to any combination of radiation, chemotherapy, immune enhancement or checkpoint inhibitors, they may live several years.”
You might be thinking, “Only several years? Why not 10 or even 20 years?”
It just doesn’t work this way. And nobody knows how far into the future an effective treatment will finally be developed – a treatment so effective that when a person gets the diagnosis of even late-stage lung cancer, the prognosis will be excellent – without losing any parts of their lungs.
Staging Results
“If all cancer is in the lung—no metastases and no spread to lymph nodes—an operation is potentially curative,” says Dr. Little.
The disease may be found in an early stage by accident when someone gets a chest X-ray for an unrelated reason, such as to check for internal damage after a car crash or for chest pain.
“If metastatic disease is found in a distant organ (liver, brain and bone are the most common locations), there is no role for surgery, as all cancer cannot be removed,” continues Dr. Little.
“If there are no metastases, and no lymph nodes are involved, but the tumor is invading the inside of the chest wall (most commonly at the lung apex, called a Pancoast tumor), an operation encompassing the lung and a segment of the chest is potentially curative.
“If there are no metastases, but lymph nodes in the area are involved, multimodality therapy is initiated.
“The patient receives a combination of both radiation and chemotherapy. If the tumor and the lymph nodes respond with dramatic shrinkage, then surgery is added for potential cure.”
Patient Status
The overall health of the patient, prior to treatment, can make treatment success difficult to achieve.
“Patients must be fit enough to tolerate/survive a lung resection,” says Dr. Little. “As most were/are smokers, organs damaged by smoking [including the heart] are evaluated.
“The heart’s status is determined by the patient’s exercise tolerance and, if necessary, function is evaluated by scans and even angiography if necessary.
“Lung function is routinely evaluated by a battery of lung function studies which contrast the patient’s breathing parameters to normal values.
“These studies inform the surgeon how much lung can safely be removed and the patient both survive the operation and have sufficient breathing capacity to expect a reasonable quality of life.
“Depending on the results, the thoracic surgeon may feel an entire lung can be removed if necessary (a pneumonectomy), a lobe is safe to extirpate (a lobectomy, the most frequently performed operation), or only a segment is safe (a segmentectomy, removal of part of a lobe).
“Ongoing success in treating stage IV and III patients has lengthened lives, but cure of these patients is quite rare. So from a curative perspective, treatment is difficult.”
 Alex Little, MD, trained in general and thoracic surgery at the Johns Hopkins University School of Medicine; has been active in national thoracic surgical societies as a speaker and participant, and served as president of the American College of Chest Physicians. He’s the author of “Cracking Chests: How Thoracic Surgery Got from Rocks to Sticks,” available on Amazon.
 Lorra Garrick has been covering medical, fitness and cybersecurity topics for many years, having written thousands of articles for print magazines and websites, including as a ghostwriter. She’s also a former ACE-certified personal trainer.
.
Top image: myupchar.com/en

Trouble Swallowing from Esophageal Cancer vs. ALS

Here is a detailed comparison by a surgeon between trouble swallowing from esophageal cancer compared to ALS.
If a person’s health anxiety is tuned more into esophageal cancer, he or she might start suspecting this disease as the reason they’ve been having difficulty swallowing, rather than a neurodegenerative condition.
Comparing the Trouble with Swallowing in Esophageal Cancer to that of ALS
“First, swallowing is a process that starts in the mouth; progresses when the tongue and oropharynx coordinate to propel food from the mouth and into the esophagus,” explains Alex Little, MD, a thoracic surgeon with a special interest in esophageal and lung cancer.
“The esophagus then has to propel the food bolus through the esophagus with peristaltic—sequential—muscular contractions, ultimately pushing it into the stomach,” continues Dr. Little.
The medical term for difficulty swallowing is called dysphagia.
“ALS is a condition of weak muscles, so patients with this disorder have trouble with what is called the oral phase of swallowing,” says Dr. Little.
“They can’t chew, nor can they eject the food from their mouth into the esophagus. If it does get into the esophagus, gravity will eventually move it along.”
When the muscles are atrophied enough from ALS, the patient can no longer take food by mouth.
• The ability to chew is impaired.
• The muscles that push food into the esophagus no longer work.
• At this stage, food will not get into the esophagus – not even applesauce.
“Esophageal cancers fill the inside ‘tube,’ the lumen, of the esophagus,” continues Dr. Little. “Food cannot pass.
“So, patients report they have no difficulty getting food from their mouth into the esophagus—the oral phase of swallowing—but the food hits a roadblock on the way down the esophagus.”
In other words, esophageal cancer doesn’t affect the oral phase of swallowing.
The symptom of dysphagia or “trouble swallowing” shows up on symptom lists for both esophageal cancer and ALS (bulbar onset).
Dr. Little explains, “Both ALS and esophageal cancer patients have dysphagia, but for different reasons and during different phases of the swallowing process.”
In esophageal cancer, “Some [food] may get through initially, but eventually nothing passes, and the patient has to vomit everything back up.”
Key Differences Between the Dysphagia of ALS and Esophageal Cancer
Trouble Swallowing from ALS
• With bulbar-onset disease, there will be other symptoms such as difficulty using the tongue, worm-like undulations of the tongue, slurred speech, strained speech, alteration in speaking pitch, hoarseness and buildup of saliva.
• With bulbar-onset, the trouble swallowing will feel like it’s coming from the throat. There will not be any chest- or neck-area symptoms caused by this.
• “Their dysphagia is difficulty clearing their mouth,” says Dr. Little.
• The feeling of dysphagia will also be present every time the patient swallows throughout the day to clear saliva.
Trouble Swallowing from Esophageal Cancer
• “EC patients have a ‘plug’ in their esophagus,” says Dr. Little. “They have no difficulty clearing their mouth.
“But food in the esophagus meets with difficulty passing the obstruction. Their oral phase is okay. Their dysphagia is during the esophageal phase of swallowing.”
• This means the symptoms of “swallowing” that the patient feels will be at neck level, rather than in the mouth or throat somewhere.
• However, esophageal cancer can cause pain in the throat, whereas ALS won’t.
• “The medical definition of swallowing includes the passage of food through the esophagus and into the stomach — and it’s during that phase that the EC patients have dysphagia.”
• Thus, the patient will feel a stuck feeling of food behind the chest or sternum, and/or in the neck where the esophagus begins.
• Another symptom is burning, pain or pressure in the chest, including when not eating.
“In fact, many of my patients — when asked — would say they had no trouble swallowing — by which they meant they could empty their mouths without any difficulty.
“But when asked what happened next, they would say the food sticks or it won’t pass through. This is dysphagia.”
Additional Symptoms of Esophageal Cancer
• Coughing or hoarseness
• Choking on food, particularly meat and bread
• Unexplained weight loss
Do you have true dysphagia?
Most causes of what seems to be a problem with swallowing are benign. One is laryngopharyngeal reflux disease (LPR).
LPR does not actually prevent food from clearing the throat and being propelled down the esophagus to the stomach. But it can cause dysphagia.
Anxiety is another cause. This is why when a person is chewing and swallowing right at the moment they receive shocking news or see something shocking, they might gag, cough and involuntarily spit out their food (or drink).
But once the alarming moment has passed, there’s no problem clearing the mouth and getting food into the stomach.
A sensation of difficulty swallowing may be present on and off throughout the day, regardless of eating, for someone suffering from LPR or intense anxiety.
If you’re being ravaged by the fear of esophageal cancer or ALS every time you eat, the anxiety WILL make swallowing seem impaired.
Diagnosis Yearly in the U.S.
- About 17,600 for esophageal cancer
- About 5,000 for ALS
SEE A DOCTOR if you have other worrisome symptoms or if symptoms are getting worse.
Alex Little, MD, trained in general and thoracic surgery at the Johns Hopkins University School of Medicine; has been active in national thoracic surgical societies as a speaker and participant, and served as president of the American College of Chest Physicians. He’s the author of “Cracking Chests: How Thoracic Surgery Got from Rocks to Sticks,” available on Amazon.
 Lorra Garrick has been covering medical, fitness and cybersecurity topics for many years, having written thousands of articles for print magazines and websites, including as a ghostwriter. She’s also a former ACE-certified personal trainer.
.
Top image: Freepik.com
Sources
hopkinsmedicine.org/neurology_neurosurgery/centers_clinics/als/conditions/als_amyotrophic_lateral_sclerosis.html
seer.cancer.gov/statfacts/html/esoph.html

Five Ways to Lower Resting Heart Rate without Drugs

If you want to lower your fast resting heart rate without drugs that can cause side effects, there are at least five natural ways to do this. (more…)
Five Ways to Stop Heart Palpitations without Drugs
A cardiologist says there are five ways you can stop heart palpitations without drugs.
If you continue having heart palpitations despite having given these five treatment methods a chance, then you should work with your cardiologist to see if perhaps a drug might be your best option. (more…)

Racing Heart vs. Irregular Heartbeat: What’s the Difference?

A racing heart isn’t always irregular, and an irregular heartbeat can sometimes be racing.
It’s important to know what the exact meaning is of these two terms, as they are often indiscriminately interchanged by writers – including those for medical sites. (more…)

Why Does Gum Disease Always Cause Bad Breath or Bleeding?

One of the first signs of gum disease is bleeding gums. Along with the inflammation and redness can be very bad breath. (more…)
What Makes Gums Look White? Could It Be Cancer?
White gums are not normal. They mean something is wrong. This includes the possibility of cancer.
Should Plus Size Women Feel Pressure to Wear a Bikini?

Are you plus size and feeling pressure to wear a bikini or other “daring” clothes due to the body positivity movement?
Have influencers convinced you that this is the only way to show the world your confidence?
They’re called “influencers” for a reason. They want to influence the thinking of their followers and gain new followers to convert.
Have you been struggling with your weight for years and are now struggling with the guilt of betraying the body positivity movement because you STILL haven’t bought a bikini or worn some other type of daring clothes that big women aren’t “supposed to wear’?
It’s as though many influencers, including morbidly obese, are shouting, “Come ON already! Take the plunge! You’ll feel liberated! A bikini body is ANY body in a bikini! What’re you waiting for?!”

Shutterstock/DenisProduction.com
But despite all the hype, all the Instagram images, all the TikTok videos — about more and more very large women showing off their bodies in bikinis — you still just can’t get into this mindset.
It’s Okay for Fat Women to Stay Covered up or Wear One-Piece Swimsuits at the Beach or Pool
You do not need to leap onto that bandwagon if the idea makes you feel uneasy or unnerved.
If you want to gain some serious empowerment, I suggest you pick up a barbell and start dripping sweat.
This is what I had my obese clients do when I was a fitness trainer.
They gained tremendous confidence knowing they were training their bodies to move heavy resistance, to climb flights of stairs with more ease, to do things that they never thought their body could do.
Since when has body positivity become a prescription for how much flesh you should show in public?
Would you buy shoes that were too small? No. Why buy a bikini if you KNOW you’ll feel uncomfortable in it?
Why not work on developing skills rather than struggling to work up the nerve to wear a bikini or crop top?
You’ll gain more empowerment and feelings of worthiness by doing any of the following:
Learning a second language, working on your speaking skills, learning to touch type, starting a garden, taking self-defense classes, learning to throw a punch, taking up yoga, volunteering for a favorite cause, learning about nutrition, spending more fun time with your kids … gee, the list is endless.
Stop worrying about the damn bikini. It’s just a prop.
Feeling Pressured to Wear a Bikini
If this is really bothering you, then you need to examine why you’ve allowed a complete stranger on Instagram to take you to this place.
Wear what feels comfortable to you. Where what feels like you.
For example, I myself would never be caught dead in a sun dress. The solution? I don’t wear sun dresses. Simple.
If you’d feel awkward, self-conscious or anything else negative in a two-piece swimsuit, or without a cover-up — then for Pete’s sake, keep wearing the one-piece with the cover-up. If for now, that’s what you feel at ease in, then DO IT.
Once you’ve made that decision, your anxiety levels will drop, and you’ll be able to focus on more important things in life than some prop.
It’s your legal and God-given right to hate wearing bikinis!
A full-figured woman has a right to be modest.
When you go to the beach or pool, you’re there to enjoy the environment, the water, play with your kids or supervise them.
You do not need to bare a lot of belly and thighs to do this.
My mother once told me, “If you have to talk yourself into buying a particular home, then it’s not the right one for you.”
Apply that to the bikini. If you have to talk yourself into wearing one in public — then the timing isn’t right for you. Ditch the idea and enjoy life.
Lorra Garrick is a former personal trainer certified through the American Council on Exercise. At Bally Total Fitness she trained women and men of all ages for fat loss, muscle building, fitness and improved health.
.
Top image: Inger Anne Hulbækdal
Seeking Chronic Pain Treatment? What Your Doctors Missed
People suffering with low back pain in the morning, neck pain or sciatica when sitting in a chair, hip pain when walking, shoulder pain or any other musculoskeletal condition…
…are still pursuing the same treatments they were seeking decades ago: (more…)